Author: Farheen Farook

  • Gum Depigmentation: Why Gums Darken and What Can Be Done

    Gum Depigmentation: Why Gums Darken and What Can Be Done

    Plenty of people like their smile until they spot it in a photo and notice dark gums. Some start smiling with their lips closed. Others worry something is wrong with their health. The truth is simpler than most people expect: dark gums are usually harmless, and when they bother you, a quick treatment called gum depigmentation can lighten them.

    Here is what causes dark gums, when they need a dentist’s attention, and how treatment works.
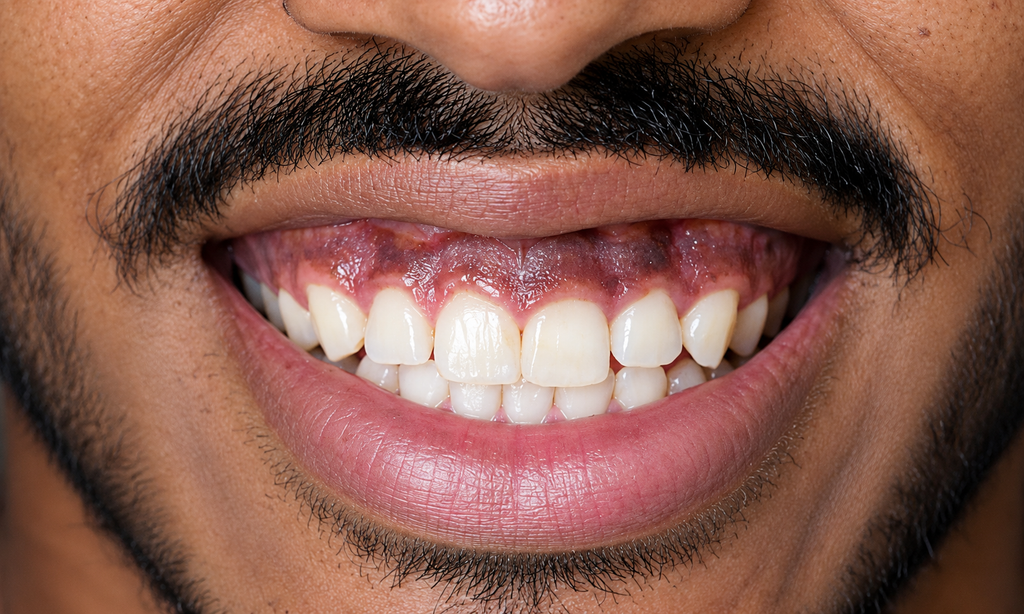
    Close-up of naturally dark gum pigmentation around a patient's upper teeth.

    Why Some Gums Are Naturally Dark

    Gum tissue contains melanin, the same pigment that gives skin, hair, and eyes their color. Your genes decide how much your gums make. People with more melanin tend to have gums that look medium brown, dark brown, or even black, usually in an even pattern. This is common in people with deeper skin tones, but it can happen with any skin tone.

    If your gums have always looked this way, feel firm, and don’t hurt or bleed, they are healthy. Dentists call this natural darkening gingival hyperpigmentation.

    What Else Can Darken Gums

    Melanin is the most common cause, but it isn’t the only one:

    • Smoking. Tobacco stimulates melanin production and can create brown or black patches. Dentists call this smoker’s melanosis.
    • Medications. Some drugs, including certain ones for acne, malaria, and other conditions, can change gum color.
    • Amalgam tattoos. Tiny particles from old silver fillings can settle in the gum and leave a small gray or black spot.
    • Gum disease. Inflamed gums often look red or purple and bleed easily. In advanced disease, dark tartar under the gumline can make the area look darker.
    • Health conditions. Some hormone-related conditions, such as Addison’s disease, can darken gums.
    • Oral melanoma. This is rare, but it explains why a new dark spot deserves a check.

    When Dark Gums Need a Dentist’s Check

    Color alone doesn’t signal disease. A change does. See your dentist soon if you notice:

    • A new dark spot that appears suddenly
    • A patch that grows, changes shape, or has uneven edges
    • A dark area that bleeds, hurts, or forms a sore that doesn’t heal within two weeks
    • A dark patch on the roof of your mouth
    • Red, swollen gums that bleed when you brush
    • Darkening that started after a new medication or after you began smoking

    Most dark spots turn out to be harmless, but your dentist should confirm that, especially before any cosmetic treatment.
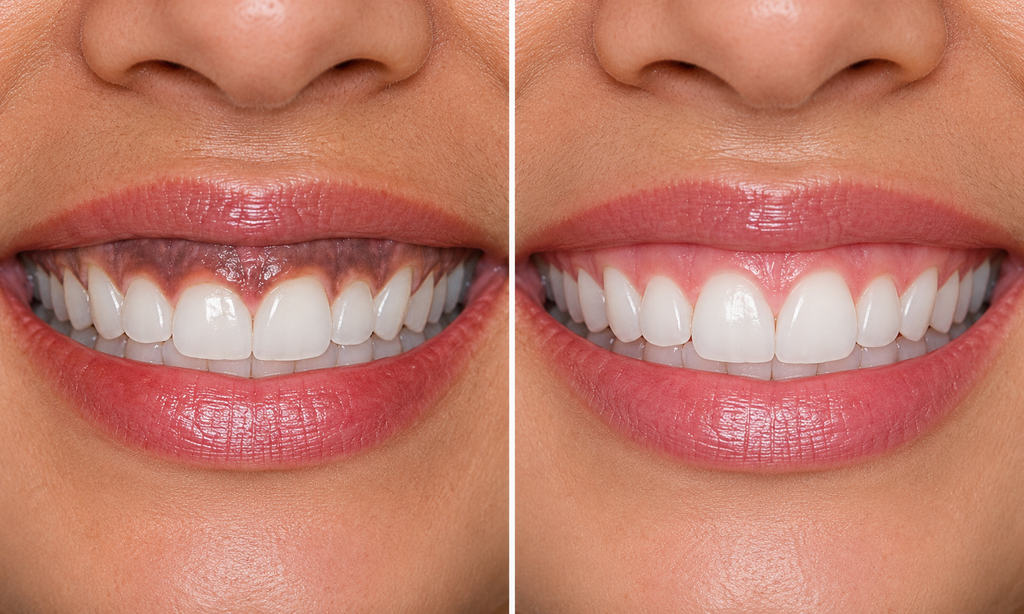
    Before-and-after comparison showing dark gum pigmentation and lighter pink gums after gum depigmentation.

    What Is Gum Depigmentation?

    Gum depigmentation, also called gum bleaching or gum lightening, is a minor procedure that removes the dark surface layer of gum tissue. As the gums heal, lighter pink tissue replaces it.

    The procedure is cosmetic, so nobody needs it for health reasons. People choose it when dark gums make them self-conscious, especially when they show a lot of gum as they smile or laugh. It isn’t the same as teeth whitening, and it doesn’t change your tooth color.

    Treatment Options

    MethodHow it worksWhat to know
    LaserA dental laser removes a thin layer of pigmented gumLittle bleeding, often no stitches, usually quick recovery
    ScalpelThe dentist cuts away the pigmented layerEffective, but usually more bleeding and a longer, more uncomfortable healing
    Diamond burA rotating tool wears away the surface layerNeeds a skilled hand
    Other methodsChemical agents, cryosurgery, electrosurgeryDentists use these less often today
    Gum graftPaler tissue from elsewhere in the mouth replaces the dark gumMore involved, so dentists save it for specific cases

    Many dentists prefer laser because it causes little bleeding and often less discomfort afterward than a scalpel. Your dentist recommends a method based on how much gum you want treated and how healthy your gums are.

    What Laser Gum Depigmentation Involves

    1. Gum check and plan. Your dentist examines your gums, treats any gum disease first, and confirms the dark color is simple pigmentation.
    2. Numbing. A local anesthetic keeps you comfortable.
    3. Laser treatment. Your dentist passes the laser over the dark areas and removes a thin layer of gum tissue.
    4. Finish. Treatment usually takes less than an hour, depending on how much gum you treat, and you go home the same day.

    Recovery and Aftercare

    Gums usually heal in about one to two weeks as new pink tissue forms. Mild tenderness and sensitivity are normal, and most people return to their routine within a day or two. To help healing:

    • Eat soft, cool foods for the first few days and avoid spicy, acidic, or very hot food
    • Brush gently with a soft toothbrush and keep the area clean
    • Avoid smoking, which slows healing and can bring the dark color back
    • Take any pain relief your dentist recommends
    • Go to your follow-up visit

    Your dentist will give you instructions that fit your treatment.

    Will the Dark Color Come Back?

    Sometimes. Pigment cells can return, and some patients see the dark color come back within months. Smoking and a strong genetic tendency raise the odds. Other people keep their results for years. No dentist can promise it lasts forever, but quitting smoking and caring for your gums helps. If color returns, your dentist can often repeat the treatment.

    Who Is a Good Candidate?

    You’re likely a good candidate if your gums are healthy, the dark color bothers you, and you understand that results vary. Active gum disease needs treatment first. A new or changing dark spot needs a check before anything else. Smokers can still have the procedure, but their results may not last as long.

    Myths About Lightening Dark Gums

    Whitening toothpaste, “gum whitening” creams, and home scrubbing don’t remove gum pigment. They can irritate or wear down your gums. Treatment from a dentist is the reliable way to lighten gum pigment.

    Frequently Asked Questions

    Q: Is gum depigmentation painful?

    A: Your dentist numbs the area first, so you shouldn’t feel pain during treatment. Your gums may feel sore or sensitive for a few days afterward. Soft foods and the pain relief your dentist suggests help.

    Q: How long do the results last?

    A: It varies. Some people keep their results for years, while others see the color return within months, especially if they smoke.

    Q: Is it safe?

    A: Dentists use lasers for gum treatments routinely, and the procedure is considered safe when a trained dentist performs it after checking your gums.

    Q: Can I have it if I smoke?

    A: Yes, but smoking can slow healing and bring the dark color back. Quitting improves your results.

    Q: How much does it cost?

    A: The price depends on how much gum you treat and which method your dentist uses. After examining your gums, your dentist gives you a clear quote.
    Dentist examining a patient's gums during a dental checkup at C Dental Clinic.

    Gum Depigmentation at C Dental Clinic

    At C Dental Clinic in Al Nahda, Sharjah, we offer gum depigmentation, also called laser gum bleaching, as part of our laser dentistry services. We start with a full gum check. If gum disease causes the color change, our periodontics team treats it first, then we plan your gum lightening.

    👉 Book a consultation at C Dental Clinic to find out whether gum depigmentation is right for you.

    References

    1. Colgate Oral Care — Black Gums: Symptoms, Causes, and Treatments
    2. National Center for Biotechnology Information — Laser-Assisted Gingival Depigmentation: A Case Report

  • Tongue-Tie in Babies: Feeding Problems and When a Frenectomy Helps

    Tongue-Tie in Babies: Feeding Problems and When a Frenectomy Helps

    Painful latching, a baby who seems hungry constantly but never quite satisfied, feeding sessions that drag on far longer than they should. These are exhausting on their own, and when a pediatrician or lactation consultant mentions “tongue-tie” as a possible cause, it’s natural to want clear answers fast: what is this, does my baby actually have it, and does it need fixing?

    Here’s what tongue-tie actually involves, how it connects to feeding difficulties, and when a frenectomy genuinely helps.

    What Tongue-Tie Actually Is

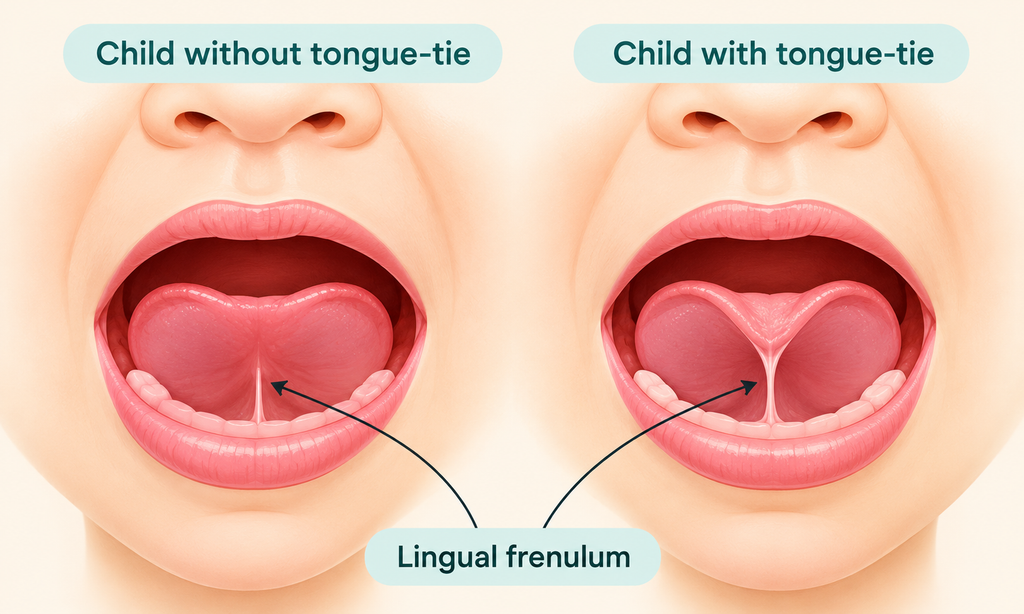
    Comparison of a child's tongue without tongue-tie and with tongue-tie, showing the restricted lingual frenulum

    Tongue-tie, medically called ankyloglossia, happens when the thin band of tissue connecting the tongue to the floor of the mouth, the lingual frenulum, is shorter or tighter than usual. That restriction limits how freely the tongue can move, which matters more than it sounds, since a baby needs full tongue mobility to latch onto a nipple and create the suction needed to feed effectively.

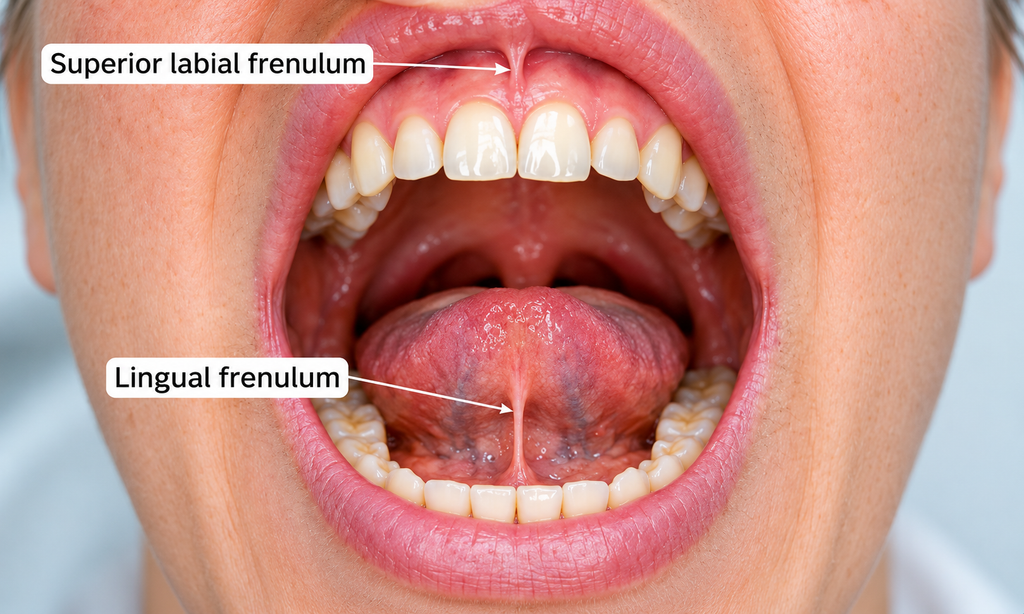
    Tongue-tie affects somewhere around 3 to 11% of newborns, depending on the study, and it’s more common in boys and firstborn children. A related condition, lip-tie, involves a tight frenulum connecting the upper lip to the gum instead, and the two sometimes occur together.

    Here’s an important point worth knowing upfront: many babies with tongue-tie have no symptoms at all. Having a short frenulum doesn’t automatically mean feeding problems follow. This matters because it shapes how a diagnosis gets approached, it’s not a condition that’s treated just because it’s present, but because it’s actually causing a problem.

    Signs Your Baby Might Have Tongue-Tie

    A few signs, in the baby and in the breastfeeding parent, tend to point toward tongue-tie as worth investigating:

    In your baby:

    • Difficulty staying latched, or popping on and off the nipple repeatedly during feeds
    • A tongue that looks notched or heart-shaped when your baby cries or sticks it out
    • Trouble lifting the tongue to the roof of the mouth, or moving it side to side
    • Unusually long feeding sessions without seeming satisfied afterward
    • Clicking sounds while feeding
    • Slow weight gain, in more significant cases

    In a breastfeeding parent:

    • Pain while nursing, beyond the normal adjustment period
    • Cracked, damaged, or misshapen nipples after feeds
    • A feeling that the baby is chewing rather than properly latching

    Not every baby with tongue-tie shows all of these, and some of these signs can come from other causes entirely, like a shallow latch unrelated to the tongue at all. That’s exactly why a proper evaluation matters more than trying to diagnose it from a symptom checklist at home.

    How Tongue-Tie Gets Diagnosed

    Illustration identifying the superior labial frenulum and lingual frenulum inside the mouth

    A pediatrician, lactation consultant, or dentist examines your baby’s mouth directly, checking how far the tongue extends, how it moves, and the appearance of the frenulum itself. Often, this evaluation happens alongside a broader look at the whole feeding relationship, since latch problems can come from several directions at once, not tongue-tie alone.

    This combined approach matters. The research on tongue-tie is genuinely mixed, some studies show clear improvement in feeding after treatment, while others find no strong evidence that frenectomy alone extends breastfeeding duration. That’s not a reason to dismiss the diagnosis, it’s a reason a thorough evaluation, rather than treatment based on appearance alone, leads to better decisions.

    What a Frenectomy Actually Involves

    A frenectomy (sometimes called a frenotomy) releases the tight frenulum, giving the tongue, or lip, more room to move freely. For infants, it’s typically a quick, simple procedure:

    • A dentist or specialist examines the frenulum and confirms it’s contributing to the feeding difficulty
    • Using sterile scissors or a laser, the frenulum is released in a procedure that usually takes just a few minutes
    • Minimal to no anesthesia is generally needed for infants, given how brief the procedure is
    • Breastfeeding often resumes within minutes afterward, which also helps soothe your baby

    Laser frenectomy has become increasingly common for this age group, since it tends to involve less bleeding and a smoother recovery compared to traditional scissors.

    What Happens After

    Most families notice some improvement in latch and feeding comfort fairly quickly, though it isn’t always instant, and tongue function sometimes needs a bit of practice to catch up with the new range of motion. Gentle stretching exercises are sometimes recommended afterward to prevent the area from reattaching as it heals, your dentist will walk you through exactly what that looks like if it applies to your baby.

    Complications are rare, but it’s still a minor procedure worth having done by someone experienced specifically with infant frenectomies, given how small and delicate the area is at that age.

    Does Every Tongue-Tie Need Treatment?

    Not necessarily. Since many babies with a tight frenulum feed just fine, a “wait and see” approach is sometimes reasonable, particularly for mild cases without clear feeding difficulty. The decision to treat comes down to whether tongue-tie is actually causing a functional problem, not simply whether it’s present.

    This is worth discussing directly with your pediatrician, lactation consultant, and dentist together, since feeding difficulties sometimes resolve with latch coaching and positioning changes alone, without needing a procedure at all.

    Frequently Asked Questions

    Q: Is a frenectomy painful for my baby?

    A: The procedure itself is brief, and infants typically have very few nerve endings in this specific tissue. Most babies cry briefly from being held still rather than from pain, and settle quickly once feeding resumes.

    Q: Will tongue-tie fix itself as my baby grows?

    A: It doesn’t typically resolve on its own, since the frenulum doesn’t change shape with growth. Some babies simply adapt well enough that it never causes a noticeable problem, which is different from it going away.

    Q: What if my baby is older, is it too late for a frenectomy?

    A: No. Frenectomies are performed at various ages, including in older children when tongue-tie affects speech, eating, or dental alignment rather than feeding specifically.

    Q: Can lip-tie cause feeding problems too?

    A: Yes, on its own or alongside tongue-tie. An upper lip-tie can affect how well a baby seals around the nipple, and some babies benefit from treating both together if both are contributing to feeding difficulty.

    Q: Should I see a lactation consultant or a dentist first?

    A: Either is a reasonable starting point, and many families end up working with both. A lactation consultant can help assess the overall feeding relationship, while a dentist evaluates and treats the frenulum itself if a procedure is needed.

    Dentist examining a child's mouth using dental instruments during an oral examination

    Infant Frenectomy at C Dental Clinic

    At C Dental Clinic in Al Nahda, Sharjah, every infant frenectomy evaluation looks at the full feeding picture, not just the appearance of the frenulum, so you get a clear answer on whether treatment will actually help your baby before anything is done.

    Our pediatric dentistry team also provides children’s dental care and helps parents understand oral health concerns at different stages of childhood.

    👉 Book a consultation at C Dental Clinic if you’re concerned about tongue-tie or feeding difficulties.

    References

    1. Mayo Clinic Health System — Tongue-Tie Symptoms and Treatment
    2. Children’s Hospital Los Angeles — Has Your Baby Been Diagnosed With Tongue-Tie?
    3. Kaiser Permanente — Tongue-Tie/Frenotomy Guide for Parents

  • Pulpotomy vs. Pulpectomy: Which Does Your Child Need?

    Pulpotomy vs. Pulpectomy: Which Does Your Child Need?

    Hearing that your child needs a “baby root canal” tends to trigger two reactions at once: relief that the tooth can be saved, and confusion about what the procedure actually involves. To make it more confusing, dentists use two different terms, pulpotomy and pulpectomy, somewhat interchangeably in casual conversation, even though they’re genuinely different procedures.

    Understanding the difference helps you know what to expect, and helps you ask your dentist the right questions before treatment.

    Why Baby Teeth Sometimes Need This at All

    Baby teeth have proportionally larger pulp chambers than adult teeth, the soft inner tissue containing nerves and blood vessels. That makes them more vulnerable once decay or damage reaches that inner layer. When a cavity goes untreated, or a tooth gets damaged from an injury, bacteria can reach the pulp and cause infection or inflammation.

    At that point, your dentist has a decision to make: treat the pulp to save the tooth, or extract it. In most cases, saving the baby tooth is the better outcome, since baby teeth hold space for permanent teeth, guide them into proper position, and support normal chewing and speech development until they naturally fall out.

    A pediatric dentist is specially trained to assess children’s developing teeth and recommend appropriate treatments, including pulpotomy and pulpectomy.

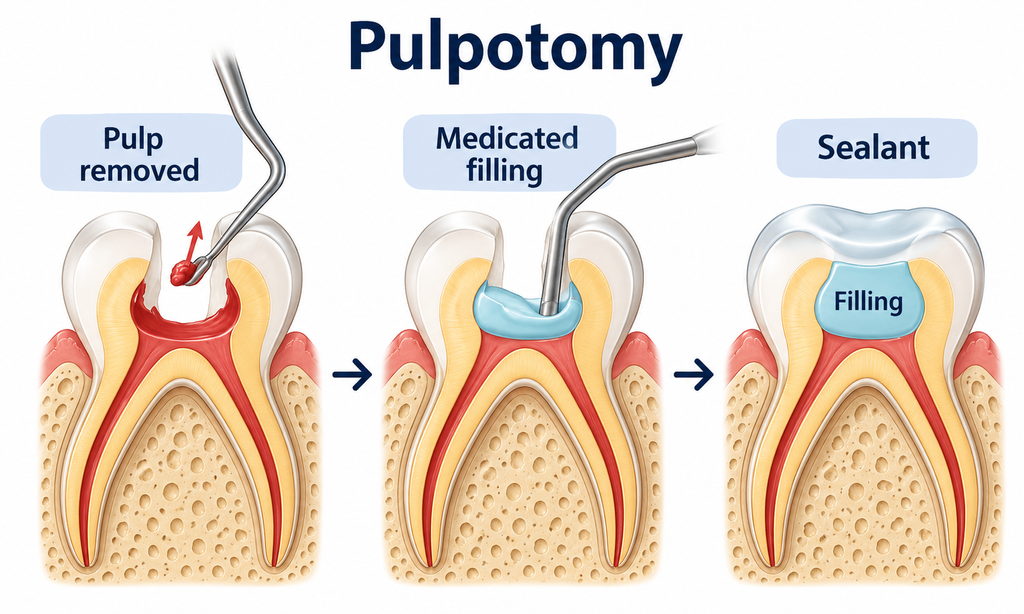
    Dental diagram showing the three stages of a pulpotomy, including removal of damaged pulp, medicated filling, and tooth sealing.

    What a Pulpotomy Actually Is

    A pulpotomy treats only the upper portion of the pulp, the part inside the crown of the tooth. Your dentist removes the damaged or infected tissue from that top section, leaves the healthy pulp in the root intact, and seals the area with a medicated material to protect what remains. A stainless steel crown or filling usually finishes the tooth off.

    This is the more conservative option, and it works well when the infection or damage hasn’t reached down into the root canals yet. It’s most commonly done on baby molars, which have more pulp tissue and a higher chance of this kind of exposure.

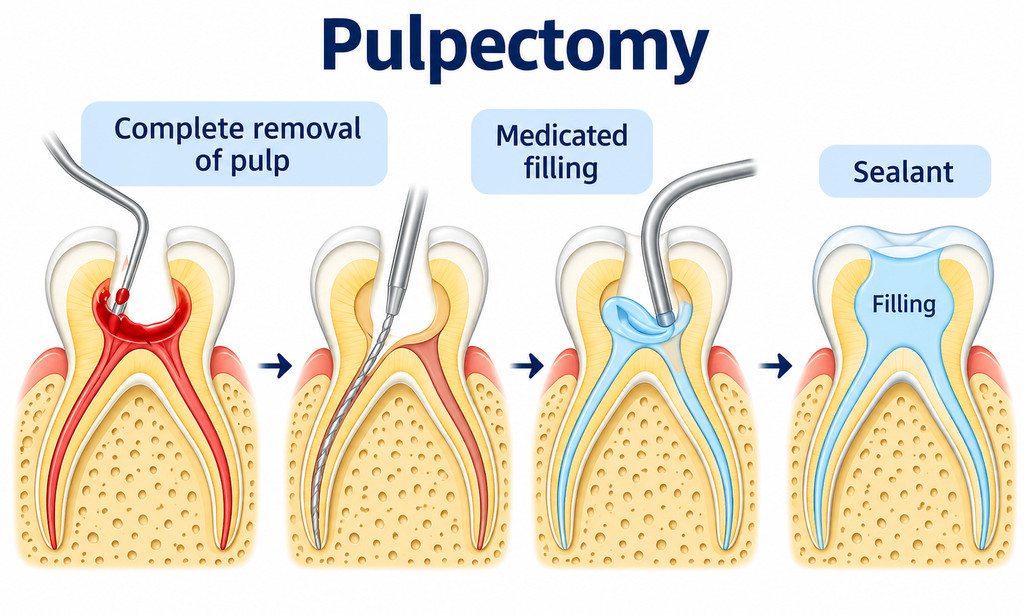
    Dental diagram illustrating pulpectomy stages, from complete pulp removal and canal cleaning to medicated filling and sealing.

    What a Pulpectomy Actually Is

    A pulpectomy goes further. If the infection has spread into the root canals themselves, or the pulp throughout the entire tooth is too damaged to leave any of it in place, your dentist removes all of the pulp, crown and root both. The canals get cleaned, disinfected, and filled with a material designed specifically for baby teeth, since it needs to resorb naturally as the tooth eventually falls out on its own. A crown typically completes the restoration here too.

    Essentially, a pulpectomy functions like a full root canal, just adapted for a tooth that’s going to exfoliate eventually rather than stay in your child’s mouth forever.

    The Core Difference, Simply Put

    PulpotomyPulpectomy
    What’s removedPulp from the crown onlyPulp from the crown and the roots
    When it’s usedPartial infection, healthy pulp remains in the rootInfection has spread through the entire tooth
    Procedure extentLess invasive, shorterMore involved, similar to an adult root canal
    GoalSave the tooth, preserve healthy tissue belowSave the tooth despite more extensive damage

    Both procedures share the same underlying goal: save the baby tooth rather than extract it, whenever that’s a realistic option.

    How Your Dentist Decides Which One Your Child Needs

    This isn’t guesswork. Your dentist bases the decision on a combination of factors:

    • Symptoms. Mild, occasional sensitivity points toward a more contained problem. Persistent pain, swelling, or a visible gum abscess suggests the infection has progressed further.
    • X-rays. Imaging shows exactly how far decay or infection has spread, including whether it’s reached the root canals.
    • Bleeding during the procedure. If your dentist starts a pulpotomy and finds excessive bleeding or clearly infected tissue in the root canals once the crown portion is treated, that’s often a sign the plan needs to shift toward a full pulpectomy instead.
    • Overall tooth condition. Enough healthy tooth structure needs to remain to support a restoration afterward, regardless of which procedure is used.

    Sometimes a dentist won’t know for certain which procedure is needed until partway through treatment, which is completely normal and part of why these decisions happen in real time rather than purely from an X-ray beforehand.

    What to Expect Afterward

    Recovery from both procedures tends to be quick. Mild soreness for a day or two is normal, usually manageable with the pain relief your dentist recommends. Most children return to normal eating and activities within a day or so, and both procedures are generally well tolerated even in younger kids.

    The restored tooth, whether finished with a filling or a stainless steel crown, functions normally afterward, letting your child chew, speak, and smile without the issue that brought them in.

    What Happens If You Skip Treatment Entirely

    It’s worth understanding why extraction isn’t automatically the simpler choice. Pulling a baby tooth too early can let neighboring teeth drift into the empty space, which sometimes crowds or misaligns the permanent tooth trying to come in underneath. It can also affect your child’s ability to chew properly on that side and, in some cases, impact speech development if front teeth are involved. A pulpotomy or pulpectomy, when the tooth can realistically be saved, generally supports better long-term outcomes than early extraction.

    Frequently Asked Questions

    Q: Is a pulpotomy or pulpectomy painful for my child?

    A: Both are done under local anesthesia, so your child shouldn’t feel pain during the procedure. Mild soreness afterward is normal and typically resolves within a day or two.

    Q: Will my child need a crown afterward either way? 

    A: Often, yes. Baby teeth treated with either procedure usually need a crown or filling to restore strength and function, since the tooth structure has been weakened by the decay or infection in the first place.

    Q: Can a pulpotomy turn into a pulpectomy during the same visit? 

    A: Yes, this happens fairly often. If your dentist finds more extensive infection than expected once treatment begins, the plan may shift to a pulpectomy in the same appointment to properly address it.

    Q: Does the filling material in a pulpectomy stay in permanently? 

    A: No. The material used in a baby tooth pulpectomy is specifically designed to resorb naturally as the tooth eventually loosens and falls out, unlike the permanent material used in an adult root canal.

    Q: How do I know if my child’s tooth pain means they need one of these procedures? 

    A: Persistent pain, swelling, a visible bump on the gum, or sensitivity that doesn’t improve are all signs worth having checked. An exam and X-ray give your dentist the clearest picture rather than guessing from symptoms alone.

    Pediatric dentist examining a young child's teeth during a dental checkup.

    Pediatric Pulp Treatment at C Dental Clinic

    At C Dental Clinic in Al Nahda, Sharjah, every pulpotomy or pulpectomy decision starts with a proper exam and X-ray, so your child gets exactly the treatment their tooth actually needs, nothing more invasive than necessary. Our pediatric dentistry team walks you through the plan clearly at every step.

    👉 Book a consultation at C Dental Clinic if your child is dealing with tooth pain or a dental injury.

    References

    1. Cleveland Clinic — Pulpotomy vs. Pulpectomy: What’s the Difference?
    2. American Academy of Pediatric Dentistry — Pulp Therapy for Primary Teeth
    3. Colgate Oral Care — Baby Root Canals: What Parents Should Know

  • What a Hollywood Smile Actually Involves

    What a Hollywood Smile Actually Involves

    “Hollywood Smile” gets thrown around a lot, on clinic websites, in ads, in casual conversation about celebrities. But ask most people what it actually involves, and the answer gets vague fast. Is it just whitening? A full set of veneers? Something else entirely?

    It’s worth clearing up, because a Hollywood Smile isn’t one specific procedure. It’s a coordinated plan, and understanding what actually goes into it makes the whole process far less mysterious.

    What a Hollywood Smile Actually Is

    A Hollywood Smile is a full smile makeover, not a single treatment. Rather than fixing one tooth or one issue, it’s a combination of cosmetic procedures planned together to create a bright, symmetrical, naturally proportioned smile, one designed around your specific face, not a generic template.

    That’s the key distinction from getting a few veneers. Veneers on their own are a spot treatment, addressing a chip, a stain, or a gap on one or two teeth. A Hollywood Smile looks at the whole picture: tooth color, shape, alignment, gum line, and how all of it works together when you smile.

    What’s Actually Included

    Depending on what your teeth need, a Hollywood Smile can combine any of the following:

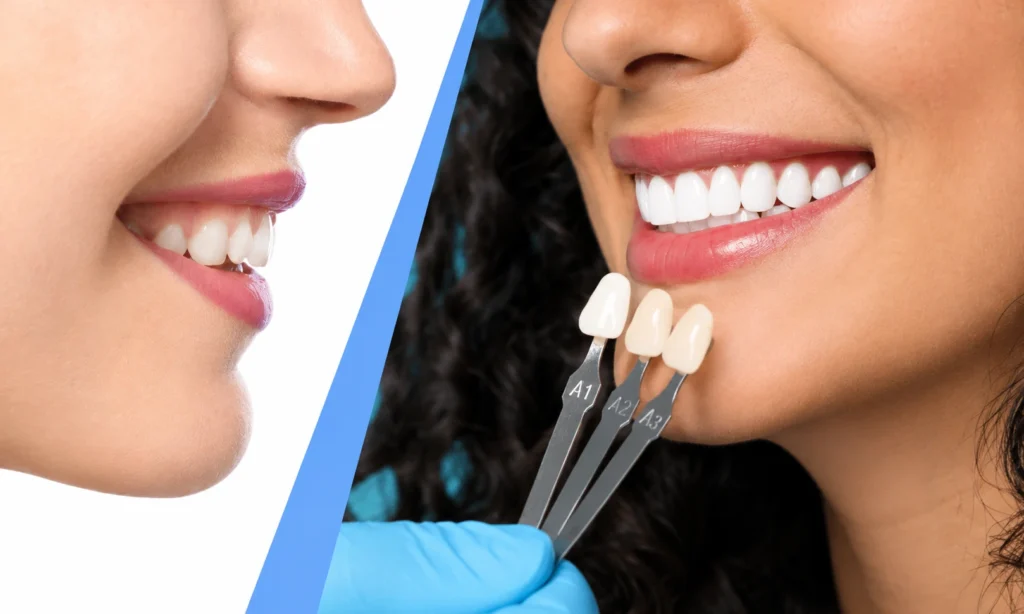
    Teeth whitening. Often the first step, since it establishes the baseline shade everything else gets matched to. If whitening happens after veneers are placed instead of before, the shades won’t align properly, which is why the order matters.

    Porcelain veneers. Thin custom shells bonded to the front of your visible teeth, usually the top 6 to 10, to correct color, shape, size, and minor alignment issues all at once.

    Dental crowns. For teeth that need more than a thin veneer can offer, whether from more significant damage or a need for extra structural support, a crown covers the entire tooth rather than just the front surface.

    Gum contouring. If your gum line looks uneven or shows more gum tissue than tooth when you smile, reshaping the gum line can make a real difference in how balanced the final result looks.

    Digital Smile Design (DSD). Modern planning increasingly starts here. Using photos and digital imaging, your dentist maps out how your new smile will actually look on your face before any tooth preparation even begins, so you’re reviewing and approving a realistic preview rather than hoping for the best.

    Not every Hollywood Smile plan uses every item on this list. Your dentist builds the combination around what your teeth and smile actually need.

    Side-by-side comparison of a smile before and after dental veneers, showing different tooth shades using a dental shade guide.

    Hollywood Smile vs. Veneers: What’s the Real Difference?

    This comes up constantly, and it’s a fair question since veneers are usually part of a Hollywood Smile anyway.

    Veneers alone are a targeted fix. If you have one chipped tooth or a stain that whitening won’t touch, veneers on just that tooth (or a small handful) solve the specific problem.

    A Hollywood Smile is broader by design. It typically covers all your visible teeth, factors in gum line and facial symmetry, and often combines veneers with whitening or contouring rather than relying on one treatment alone. It costs more and takes more planning, but the result is a coordinated transformation rather than a single correction.

    Neither is “better” in general. If you only have one problem tooth, a full Hollywood Smile is more than you need. If you want a complete, evened-out smile across all your visible teeth, that’s exactly what it’s built for.

    What the Process Actually Looks Like

    Consultation and planning. Your dentist examines your teeth, gums, and bite, discusses what you want to change, and often uses digital smile design to show you a realistic preview of the result.

    Preparation. For veneers, this usually means a small amount of enamel removal to create a flush surface. Whitening, if included, generally happens at this stage too, before your teeth are shade-matched for the final veneers.

    Impressions and temporaries. Your dentist takes precise impressions or digital scans to have your custom veneers or crowns made, and you’ll typically wear temporary versions while the final ones are being crafted.

    Final placement. Once your permanent veneers or crowns are ready, your dentist checks the color, shape, fit, and bite carefully before bonding everything into place and polishing for that final, natural-looking finish.

    How Long Does It Take?

    This varies with how much is involved. A straightforward plan using mostly veneers and whitening might wrap up in a few visits over a couple of weeks. A more complex plan involving crowns, gum contouring, or orthodontic work beforehand takes longer, sometimes a few months, since certain steps need healing time before the next stage.

    Frequently Asked Questions

    Q: Does a Hollywood Smile look fake?

    A: Not when it’s done well. A properly planned Hollywood Smile is matched to your facial proportions, skin tone, and natural tooth shade, which is exactly what digital smile design helps avoid, an overly uniform, obviously artificial look.

    Q: Is a Hollywood Smile permanent?

    A: Porcelain veneers and crowns are considered a long-term, largely permanent change, since enamel removal isn’t reversible. Whitening and gum contouring are more temporary or gradual in comparison, and your dentist will walk you through which parts of your specific plan are permanent versus not.

    Q: How many teeth are usually involved?

    A: Most Hollywood Smile plans focus on the teeth visible when you smile, typically the upper 6 to 10 front teeth, sometimes extending to the lower arch depending on your goals.

    Q: Does it hurt?

    A: Any enamel preparation is done with local anesthesia, so you shouldn’t feel pain during the procedure itself. Mild sensitivity afterward is normal and typically settles within a few days.

    Q: How do I know what my Hollywood Smile plan should include?

    A: That’s exactly what the consultation and digital smile design step are for. Rather than guessing, your dentist evaluates your specific teeth, gums, and goals, then builds a plan around what will actually make the biggest difference for your smile.

    Dentist examining a patient's teeth during a Hollywood Smile consultation at a dental clinic.

    Hollywood Smile at C Dental Clinic

    At C Dental Clinic in Al Nahda, Sharjah, a Hollywood Smile plan starts with understanding what you actually want your smile to look like, then combining the right mix of veneers, teeth whitening, and gum contouring to get there, rather than applying the same package to every patient.

    👉 Book a consultation at C Dental Clinic to find out what a Hollywood Smile plan would look like for you.

    References

    1. Cleveland Clinic — Veneers: Types, Procedure, and Care
    2. American Academy of Cosmetic Dentistry — Smile Makeover Overview
    3. Colgate Oral Care — What Is a Smile Makeover?
  • Veneers vs. Lumineers: A Real Comparison

    Veneers vs. Lumineers: A Real Comparison

    Both promise the same thing: a brighter, more even smile, fast. But “veneers” and “Lumineers” get used almost interchangeably online, which makes choosing between them harder than it should be. They’re related, not identical, and the real difference comes down to a few practical factors that actually affect how they look, how long they last, and what happens to your natural teeth along the way.

    What Each One Actually Is

    Porcelain veneers are thin custom shells, roughly 0.5 to 0.7 millimeters thick, bonded to the front of your teeth to cover chips, stains, gaps, or uneven shapes. To make room for that thickness and create a flush, natural-looking fit, your dentist removes a small amount of enamel before bonding them in place.

    Lumineers are a specific, patented brand of ultra-thin porcelain veneer, made from a material called Cerinate. At roughly 0.2 to 0.3 millimeters, they’re noticeably thinner, often compared to the thickness of a contact lens. That thinness is the whole point: Lumineers usually need little to no enamel removal at all, which is why they’re often called “no-prep veneers.”

    In short, Lumineers are a type of veneer, not a completely separate category. The difference that matters comes down to thickness, and everything else follows from that.

    The Four Differences That Actually Matter

    1. How much of your tooth gets prepared Traditional veneers require light enamel reduction to fit properly and sit flush against your tooth. Lumineers, because they’re so much thinner, usually skip this step entirely. That makes Lumineers a more conservative option if keeping your natural enamel intact matters to you, and in many cases the process is reversible, since there’s less permanent tooth alteration involved.

    2. How natural they look on discolored teeth This is where thickness works against Lumineers a little. Their thinness makes them slightly translucent, which is great for a subtle look but means they’re not always the strongest option for covering significant discoloration or a noticeably dark tooth underneath. Traditional veneers, being thicker and more opaque, generally do a better job fully masking heavier staining or damage.

    3. How long they last Both options hold up well with proper care, but traditional veneers generally edge ahead on pure durability, typically lasting 10 to 15 years or more, compared to roughly 8 to 12 years for Lumineers. The gap isn’t huge, but if you grind your teeth or want the longest possible lifespan from the investment, thicker, traditional veneers tend to hold up better under that kind of pressure.

    4. What it costs Lumineers are often slightly less expensive upfront, mainly because the procedure involves less prep work and chair time. That said, the price ranges for both genuinely overlap quite a bit depending on the case, and the “cheaper” option today can even out over time if it needs replacing sooner than a traditional veneer would. Cost shouldn’t be the only factor in the decision.

    Which One Actually Fits You?

    A few rough guidelines, though your dentist will always confirm this properly based on an in-person exam:

    • If you have minor to moderate discoloration, small gaps, or slightly uneven teeth, and you’d prefer to keep as much natural enamel as possible, Lumineers are often a strong fit.
    • If you’re dealing with more significant staining, chips, or want maximum durability and coverage, traditional porcelain veneers usually deliver a more reliable, longer-lasting result.
    • If you grind your teeth at night, thicker, traditional veneers generally hold up better against that repeated pressure than the thinner Lumineers option.
    • If reversibility matters to you, meaning you’d like the option to remove them later without permanently altering your teeth, Lumineers’ no-prep approach keeps that door open in a way traditional veneers don’t.

    Neither option is objectively “better” across the board. The right choice depends on what your teeth actually need and what you personally value, natural enamel preservation, maximum durability, or the lightest possible touch.

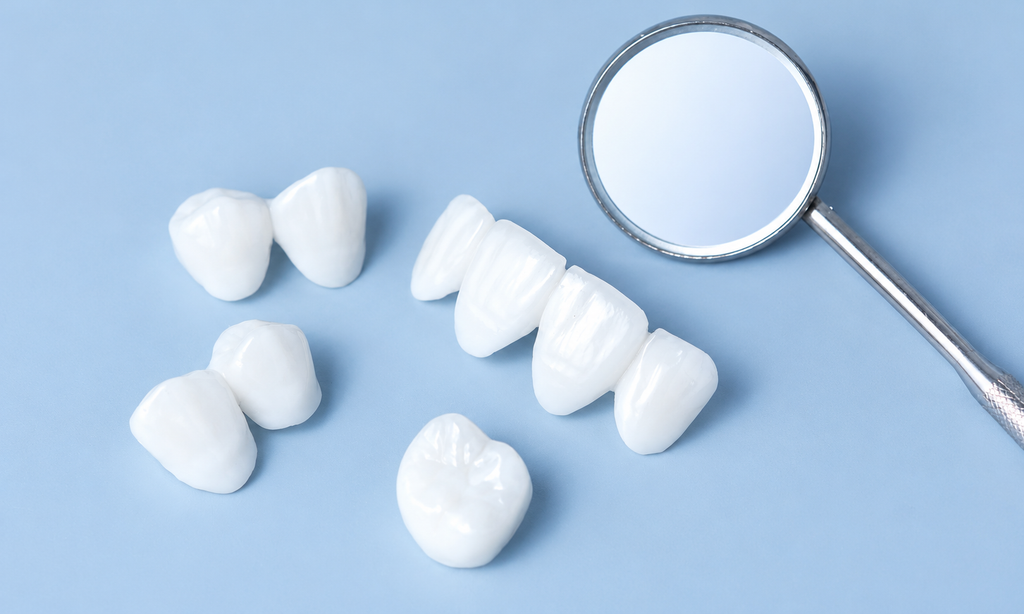
    Porcelain dental crowns displayed beside a dental mirror on a blue background.

    What Both Options Have in Common

    It’s worth remembering how much overlap exists too. Both are custom-made from porcelain, both are color-matched to blend naturally with your smile, both require a proper consultation and impression process before placement, and both need the same basic care afterward, good oral hygiene, avoiding using your teeth as tools, and regular checkups to keep an eye on their condition over the years.

    Frequently Asked Questions

    Q: Can I switch from Lumineers to traditional veneers later if I change my mind?

    A: Often, yes, since Lumineers require minimal to no enamel removal, there’s usually more natural tooth structure left to work with if you want to upgrade to traditional veneers down the line.

    Q: Do Lumineers feel different in my mouth?

    A: Most people describe them as feeling very close to natural teeth, sometimes even less noticeable than traditional veneers at first, since there’s less change to the tooth’s original shape and thickness underneath.

    Q: Which option is more painful to get?

    A: Neither should cause significant pain. Traditional veneers may involve a small amount of local anesthetic for the enamel-reduction step, while Lumineers, requiring little to no reduction, are often placed with little to no anesthesia needed at all.

    Q: Can either option fix crooked teeth?

    A: Both can visually improve mild misalignment by adjusting the shape and angle of the visible tooth surface, but neither actually moves teeth. Significant crowding or bite issues usually need orthodontic treatment first.

    Q: How do I know which one is right for my specific teeth?

    A: This really does need an in-person exam. Your dentist checks your enamel condition, the extent of discoloration, your bite, and your goals before recommending one over the other, rather than a generic rule applying to everyone.

    Veneers and Lumineers at C Dental Clinic

    Dentist comparing tooth shades with a dental shade guide against a patient's teeth during cosmetic dental treatment.

    At C Dental Clinic in Al Nahda, Sharjah, choosing between porcelain veneers and Lumineers starts with a proper look at your teeth, not a one-size-fits-all recommendation. We’ll walk you through exactly what each option means for your specific case, so the decision actually fits your smile and your priorities.

    👉 Book a consultation at C Dental Clinic to find out which option is right for you.

    References

    1. Cleveland Clinic — Veneers: Types, Procedure, and Care
    2. American Academy of Cosmetic Dentistry — Veneers and Lumineers Explained
    3. Colgate Oral Care — Lumineers vs. Veneers: What’s the Difference

  • Dentures 101: Full, Partial, and What Actually Fits Your Life

    Dentures 101: Full, Partial, and What Actually Fits Your Life

    Losing teeth, whether from decay, gum disease, or an injury, brings up a practical question fast: what actually replaces them? Dentures have been doing that job for over a century, and modern ones look nothing like the stiff, obviously-fake versions people picture. The real question isn’t whether dentures work. It’s which type actually fits your situation, and what living with them day to day really involves.

    Full Dentures vs. Partial Dentures: The Core Difference

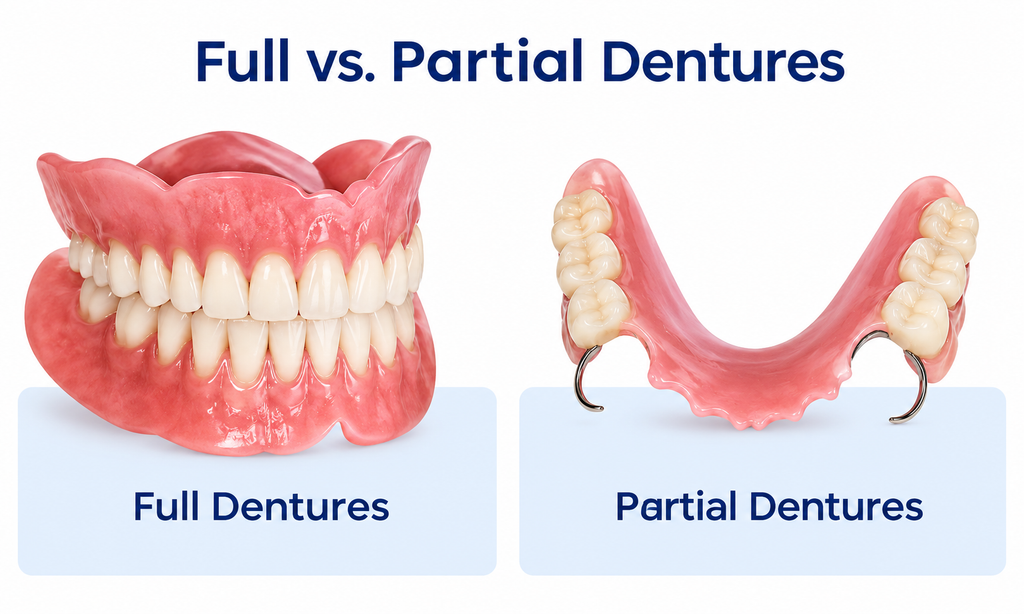
    Full dentures replacing a whole arch beside a partial denture with metal clasps for remaining natural teeth

    The choice between full and partial dentures comes down to one simple factor: how many of your natural teeth remain, and how healthy they are.

    Full dentures replace an entire arch, upper, lower, or both, when no natural teeth remain in that arch. They rest directly on your gums, held in place by suction and the natural contours of your mouth, sometimes with the help of an adhesive.

    Partial dentures fill in gaps when you still have healthy natural teeth worth keeping. They attach to those remaining teeth using small clasps or precision attachments, filling the missing spaces while leaving your healthy teeth in place and functioning.

    Neither option is automatically “better.” Your dentist bases the recommendation on the condition of whatever teeth you still have, not a general preference for one type over the other.

    Full Dentures: What to Expect

    If you’re losing all your teeth in an arch, either already gone or scheduled for extraction, your dentist typically waits a few weeks after extraction for your gums to heal before fitting a conventional full denture. In some cases, an immediate denture gets placed the same day as extraction, so you’re never without teeth, though it usually needs adjusting later as your gums finish healing and change shape.

    The fitting process involves several appointments: an exam, impressions of your gums, a bite registration to capture how your jaws align, and a tooth-shade selection to match your natural coloring. Your dentist reviews the fit and adjusts it before finalizing.

    The adjustment period genuinely takes time, usually a few weeks, sometimes longer for the lower arch specifically, since lower dentures have less surface area to grip onto and tend to feel less stable at first. Expect some soreness, increased saliva production, and speech that feels slightly off initially. This settles down with practice. Reading out loud for a few minutes a day speeds up the adjustment to speaking clearly again.

    Partial Dentures: What to Expect

    A partial denture works differently because it has something to hold onto, your remaining natural teeth. This generally makes the fitting process feel more secure from the start, and most people adjust faster than they would with a full denture, often within days to two weeks rather than a few months.

    The appliance itself consists of replacement teeth attached to a metal or flexible framework, which clips onto your natural teeth using small clasps. Depending on the design, these clasps may be slightly visible when you smile, something worth discussing with your dentist if appearance is a priority, since some partial designs minimize this more than others.

    A genuine advantage of partial dentures: keeping your remaining healthy teeth in place helps preserve your jawbone density in that area and gives your bite more natural stability than a full denture resting on gums alone.

    Comfort, Eating, and Speaking: The Practical Side

    Both types take an adjustment period, that’s simply part of wearing any removable appliance for the first time. A few practical things help regardless of which type you have:

    • Start with soft foods for the first week or two, gradually working back to your normal diet as you get used to chewing with the new appliance
    • Cut food into smaller pieces at first, and chew slowly on both sides evenly rather than favoring one side
    • Practice speaking by reading aloud, most people regain clear speech within one to two weeks
    • Expect some extra saliva production initially, this is completely normal and settles as your mouth adjusts

    If a denture ever feels genuinely painful rather than just unfamiliar, that’s not something to push through. Persistent sore spots usually mean the fit needs a quick adjustment, not that you need to simply get used to it.

    Caring for Your Dentures

    Daily care matters just as much as the fitting itself, for both types:

    • Remove and rinse your denture after eating, especially after sticky or hard foods
    • Brush it daily with a denture-specific brush and cleaner, not regular toothpaste, which can be too abrasive
    • Soak it overnight in a denture-soaking solution to keep it from drying out and losing its shape
    • If you have a partial denture, keep brushing your remaining natural teeth thoroughly, since those teeth are now doing extra work supporting the appliance and staying decay-free matters more than ever
    • Keep up with regular dental checkups so your dentist can catch fit changes early, since your gums and jawbone shift gradually over time even after the initial adjustment period

    How Long Do Dentures Last?

    With consistent care, most dentures last somewhere between five and ten years before they need replacing or relining. Full dentures on the shorter end of that range, partial dentures sometimes a bit longer, though this varies by individual. The main reason dentures eventually need replacing isn’t wear on the appliance itself, it’s that your jawbone and gums continue changing shape over the years, gradually affecting how well the original fit holds.

    Implants vs. Dentures: A Quick Note

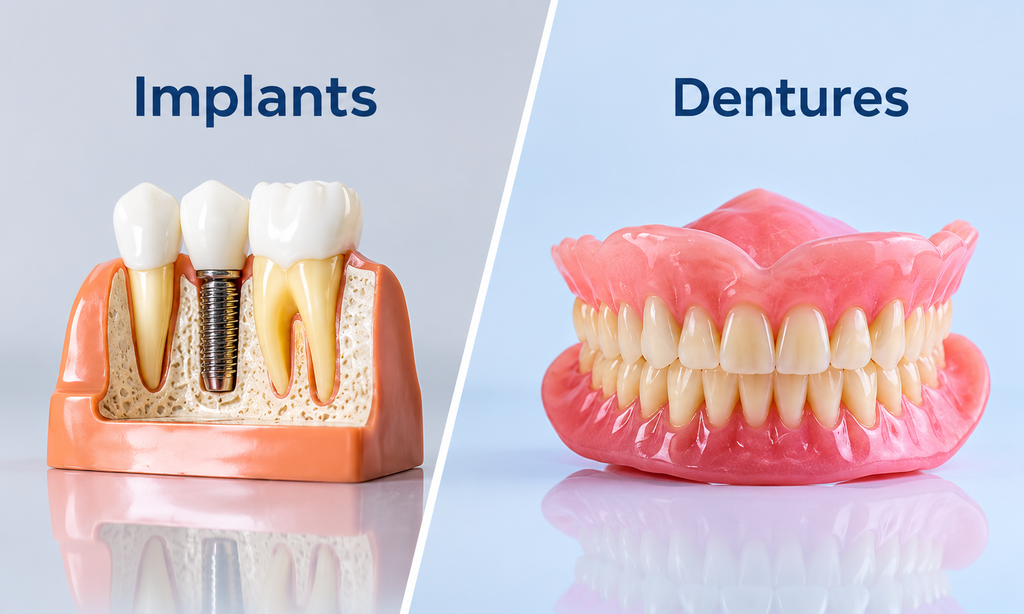
    Side-by-side comparison of a dental implant model and a set of full dentures

    Dentures aren’t the only option for replacing missing teeth. Dental implants offer a fixed, permanent alternative that doesn’t come out at night and helps preserve jawbone density more directly, since chewing pressure on an implant stimulates the bone the way a natural tooth root does. Dentures remain a strong option for many people though, particularly when cost, avoiding surgery, or replacing an entire arch at once matters more than a fixed solution. Your dentist can walk you through which fits your specific case and budget.

    Frequently Asked Questions

    Q: Will dentures look natural?

    A: Yes. Modern dentures are custom-shaded and shaped to match your natural teeth and gum color, and a well-fitted denture looks far more natural than older styles people often picture.

    Q: Can I sleep in my dentures?

    A: Most dentists recommend removing them at night to let your gums rest and to soak the denture properly, though your dentist will advise based on your specific situation.

    Q: How much do dentures cost?

    A: Cost depends on the type (full or partial), the materials used, and whether any extractions are needed first. A consultation gives you a clear, personalized estimate rather than a general figure.

    Q: What if my partial denture’s supporting tooth fails later?

    A: The partial can usually be adjusted or remade to account for the change, and in some cases it gets converted toward a full denture if enough natural teeth are eventually lost.

    Q: Can I eat normally with dentures?

    A: Yes, after the initial adjustment period. Most people return to a full, varied diet within a few weeks, starting soft and working back up to harder foods as confidence builds.

    Dentures at C Dental Clinic

    Dentist showing a denture on a tray to a smiling patient during a denture consultation at C Dental Clinics Sharjah

    At C Dental Clinic in Al Nahda, Sharjah, every denture case starts with a close look at how many teeth remain, their condition, and what actually fits your daily life, rather than defaulting to one type for everyone. Whether you need a full arch replaced or a partial to fill a few gaps, we fit and adjust each denture until it genuinely feels right.

    👉 Book a consultation at C Dental Clinic to find out which type of denture fits your situation.

    References

    1. Cleveland Clinic — Dentures: Types, Care, and What to Expect
    2. Mayo Clinic — Dentures: Getting Used to New Dentures
    3. American College of Prosthodontists — Denture Care and Facts

  • Dental Implants: What to Expect Before, During, and After

    Dental Implants: What to Expect Before, During, and After

    A missing tooth changes more than your smile. It changes how you chew, how your other teeth shift over time, and sometimes how confident you feel talking to someone up close. Dental implants exist to solve that problem properly, not just cover it up, and they’ve become the option most dentists recommend when a tooth can’t be saved.

    Still, “implant” is a word that carries a lot of anxiety. People imagine a long, painful surgery and months of uncertainty. The reality looks quite different once you understand what actually happens at each stage.

    What a Dental Implant Actually Is

    Dentist explaining a dental implant model with the titanium post, abutment, and crown to a patient

    A dental implant replaces a missing tooth in three parts. A small titanium post takes the place of the tooth’s root, sitting inside your jawbone. An abutment connects that post to the visible part of the tooth. And a custom crown sits on top, matched to your natural teeth in shape and color.

    Titanium works so well here because your jawbone actually fuses to it over time, a process called osseointegration. That fusion is what makes an implant function like a real tooth root, rather than just sitting in place the way a denture does.

    Before the Procedure: The Consultation and Planning Stage

    Your dentist starts with a thorough exam, usually including X-rays or a 3D scan, to check your jawbone density and the exact position of nerves and sinuses nearby. This step matters more than people expect. Bone quality varies from person to person, and it directly affects whether you’re a straightforward candidate or need an extra step first.

    If your jawbone has thinned out, often from a tooth that’s been missing for a while, your dentist may recommend a bone graft before placing the implant. A graft adds several months to the overall timeline, since the grafted bone needs to heal and strengthen before it can properly support an implant. Not everyone needs one. Many patients move straight to implant placement.

    At this stage, your dentist also maps out how many implants you need. A single missing tooth needs just one. Several missing teeth in a row, or a full arch, might use a bridge supported by two or more implants instead of replacing every single tooth individually, which keeps the procedure and the cost more manageable.

    During the Procedure: What Implant Surgery Actually Involves

    The placement itself is a minor oral surgery, done under local anesthesia, so you stay comfortable and awake throughout. Your dentist makes a small opening in the gum, places the titanium post directly into the jawbone, and closes the site. A single implant typically takes one to two hours.

    Most people describe the procedure as far less dramatic than they expected. The anesthesia handles the discomfort during the surgery itself, and any soreness afterward responds well to standard pain relief, similar to what you’d feel after a tooth extraction.

    Once the post is in place, the waiting begins. Osseointegration, the bone fusing to the implant, takes roughly three to six months. Lower jaw implants tend to integrate a bit faster than upper jaw ones, simply because the bone density differs between the two. This phase can’t be rushed. It’s biological, not something a dentist can speed along, and it’s the single reason the full implant process takes months rather than weeks.

    Once your dentist confirms the implant has fully integrated, a second short procedure attaches the abutment. From there, your dentist takes an impression to create your custom crown, which gets fitted and attached a few weeks later.

    After the Procedure: Healing Week by Week

    The first 24 to 48 hours bring the most noticeable swelling and tenderness, similar to recovering from an extraction. Rest, a cold compress, and the pain relief your dentist recommends keep this manageable.

    The first week calls for soft foods and gentle care around the surgical site. Most patients return to normal daily activities within a few days, though strenuous exercise usually waits until the initial swelling settles.

    Weeks two through six cover the early soft-tissue healing around the implant. Good oral hygiene matters enormously here, since keeping the area clean protects against infection while everything underneath continues fusing.

    Months two through six are mostly uneventful from your side. Osseointegration happens quietly in the background, and your dentist checks in periodically to confirm everything’s progressing as expected.

    After full integration, the abutment and crown placement finish the process, and you’re left with a tooth that looks, feels, and functions like the one it replaced.

    Is an Implant Right for You?

    Good candidates generally have healthy gums, enough jawbone to support the implant (or the willingness to graft first), and no uncontrolled conditions that would slow healing, like unmanaged diabetes or active gum disease. Smoking also significantly affects healing and integration, so your dentist will likely discuss this directly if it applies to you.

    Age alone rarely rules someone out. What matters more is overall oral and bone health, which your dentist evaluates properly during that first consultation rather than guessing from general assumptions.

    Implant vs. Bridge: A Quick Comparison

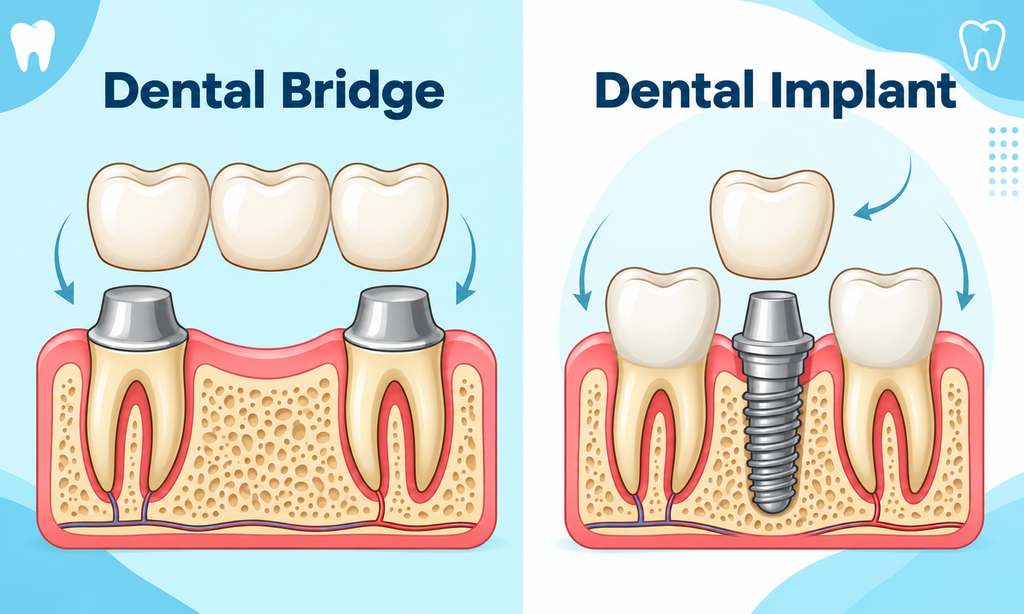
    Diagram comparing a dental bridge anchored to filed-down teeth versus a dental implant placed directly in the jawbone

    A traditional bridge replaces a missing tooth by anchoring a false tooth to the healthy teeth on either side of the gap, which means grinding down those neighboring teeth to support it. An implant doesn’t touch your surrounding teeth at all. It stands on its own, supported directly by your jawbone.

    Bridges cost less upfront and involve no surgery, which makes them appealing for some patients. Implants tend to last longer, preserve your jawbone density (since chewing pressure on the implant keeps stimulating the bone the way a natural root would), and avoid putting extra strain on healthy neighboring teeth. Your dentist can walk you through which makes more sense for your specific situation.

    If a fixed option isn’t the right fit for your situation, dentures remain a strong, flexible alternative worth discussing with your dentist.

    Frequently Asked Questions

    Q: How much does a dental implant cost?

    A: Cost varies depending on how many implants you need, whether a bone graft comes first, and the type of crown or bridge attached at the end. A single implant consultation gives you a clear, personalized estimate rather than a generic number, since every case differs.

    Q: Are dental implants painful?

    A: The surgery itself happens under local anesthesia, so you won’t feel pain during placement. Afterward, most patients describe mild to moderate soreness for a few days, similar to a tooth extraction, manageable with standard pain relief.

    Q: How long does the whole process take?

    A: From consultation to a finished crown, the full process usually spans three to eight months, mostly because osseointegration can’t be rushed. The appointments themselves take up a small fraction of that time.

    Q: Can I get an implant if I’ve been missing a tooth for years?

    A: Often, yes. Long-term tooth loss can lead to bone thinning in that area, which sometimes means a bone graft comes first. Your dentist evaluates this directly with imaging rather than assuming based on how long the tooth’s been gone.

    Q: What happens if I don’t replace a missing tooth at all?

    A: Neighboring teeth gradually shift into the gap, your bite can change, and the jawbone underneath the missing tooth slowly loses density from lack of stimulation. Replacing the tooth, whether with an implant or another option, prevents that chain reaction.

    Dental Implants at C Dental Clinic

    At C Dental Clinic in Al Nahda, Sharjah, every implant case starts with a proper evaluation of your jawbone, gum health, and overall dental history, since the right approach genuinely depends on your specific situation rather than a one-size-fits-all plan. Whether you need a single implant or a full arch, we walk you through each stage clearly before anything begins.

    👉 Book a consultation at C Dental Clinic to find out if dental implants are right for you.

    References

    1. Cleveland Clinic — Dental Implants: Procedure, Recovery, and Benefits
    2. Mayo Clinic — Dental Implant Surgery: What You Can Expect
    3. American Academy of Implant Dentistry — Dental Implant FAQs

  • Lockjaw Explained: Is It a TMJ Problem or Something More Serious?

    Lockjaw Explained: Is It a TMJ Problem or Something More Serious?

    Few words in dentistry cause as much confusion as “lockjaw.” Someone types it into a search bar expecting a straightforward answer, and instead finds two completely different conditions sharing the same name, one that’s uncomfortable but harmless, and one that’s a genuine medical emergency. Not knowing which one applies to you is unsettling, and honestly, it should be. This is one of those topics worth getting exactly right rather than guessing.

    So let’s clear it up properly.

    Lockjaw Actually Means Two Different Things-

    Here’s the part that trips almost everyone up: “lockjaw” isn’t a single diagnosis. It’s an old, informal term that has ended up describing two unrelated conditions, and the word itself gives no clue which one you’re dealing with.

    The first, and far more common, is trismus. This is when the muscles around your jaw joint tighten or spasm to the point where you can’t open your mouth fully, sometimes barely at all. It’s usually linked to the temporomandibular joint (TMJ), dental procedures, jaw injury, or muscle strain. It’s painful and frustrating, but it is not life-threatening.

    The second is tetanus, a bacterial infection that historically gave “lockjaw” its name in the first place. Tetanus causes severe, whole-body muscle spasms, starting in the jaw and neck and potentially spreading further. This one is a medical emergency, and it has nothing to do with your teeth or TMJ.

    Both get called lockjaw. Only one belongs in a conversation with your dentist. Telling them apart matters, so let’s go through each one properly.

    TMJ-Related Lockjaw (Trismus): What Causes It

    3D illustration of jaw joint pain highlighting the TMJ area

    Trismus happens when the muscles responsible for opening and closing your jaw go into spasm or become too tight to function normally. A healthy mouth typically opens somewhere between 40 and 60 millimeters. With trismus, that range often drops well below 35 millimeters, sometimes far less.

    A number of things can trigger it:

    TMJ disorder. Problems with the joint itself, including a displaced disc that physically blocks the jaw from opening fully, are among the most common causes of trismus.

    Dental procedures. This is worth knowing specifically if you’re a dental patient. Trismus can follow wisdom tooth extractions, long or difficult procedures where the jaw was held open for an extended time, or occasionally an injection of local anaesthetic that irritates nearby muscle tissue. It’s a recognized, temporary side effect rather than a sign anything went wrong.

    Jaw trauma. A blow to the face or jaw, or an injury from a fall or accident, can cause the surrounding muscles to tighten protectively.

    Muscle overuse or strain. Prolonged clenching, teeth grinding, or even a wide yawn in an awkward position can occasionally trigger a temporary spasm.

    Infections near the jaw. Dental infections, mumps, or tonsillitis can sometimes cause enough localized inflammation to restrict jaw movement.

    Radiation therapy. For patients who’ve had radiation to the head or neck area, trismus is a well-documented and fairly common side effect, sometimes appearing months after treatment ends.

    Symptoms of TMJ-Related Trismus

    Trismus tends to present in a fairly consistent way:

    • Difficulty opening your mouth fully, or being unable to open it at all in more severe cases
    • Pain or tenderness around the jaw joint, especially when trying to open wider
    • Jaw stiffness that may ease slightly with gentle movement, then return
    • Trouble chewing or swallowing certain foods
    • A history of jaw clicking or popping before the locking began, which often points toward a TMJ disc issue specifically
    • Discomfort that stays localized to the jaw and face, without spreading to the rest of the body

    If your jaw feels stuck, sore, and limited to that one area, this is almost always what you’re dealing with, and it’s very manageable.

    Tetanus Lockjaw: Why It’s a Completely Different Situation

    Tetanus is caused by a bacterial toxin, usually entering the body through a wound, cut, or puncture, particularly one that’s deep or contaminated with soil or rust. It has nothing to do with dental work or TMJ health. Thanks to widespread vaccination, it’s now uncommon in places with good healthcare access, but it hasn’t disappeared, and it remains genuinely dangerous when it does occur.

    What sets tetanus apart from TMJ-related trismus is that the muscle spasms don’t stay in the jaw. Warning signs include:

    • Jaw stiffness that progresses quickly and severely
    • Spasms spreading to the neck, chest, back, or stomach
    • Difficulty swallowing alongside the jaw symptoms
    • Muscle rigidity or spasms triggered by light, sound, or touch
    • Fever, sweating, or a noticeably elevated heart rate
    • A stiff, unusual facial expression sometimes described as a forced smile

    If any of this sounds like what you’re experiencing, especially alongside a recent wound, cut, or injury, particularly if your tetanus vaccination isn’t up to date, this is not something to wait out or treat at home. It requires emergency medical care immediately, not a dental appointment.

    How to Tell Them Apart

    A simple way to think about it: TMJ-related lockjaw stays local. It’s confined to your jaw, face, and sometimes your neck, and while it’s uncomfortable, you generally still feel like yourself otherwise. Tetanus spreads. It moves beyond the jaw, comes with symptoms like fever and full-body muscle stiffness, and tends to get noticeably worse over hours or days rather than staying the same.

    If you’re ever unsure, treat it as urgent and get evaluated rather than guessing. A doctor or emergency room can rule out tetanus quickly, while a dentist can properly diagnose and treat TMJ-related trismus.

    Treating TMJ-Related Lockjaw

    The reassuring part is that trismus, once confirmed as TMJ or muscle-related rather than tetanus, responds well to fairly conservative treatment:

    • Gentle jaw stretching exercises, often guided by a dentist or physical therapist, to gradually restore range of motion
    • Moist heat applied to the jaw to relax tight muscles
    • Anti-inflammatory medication or, in some cases, a short course of muscle relaxants
    • A custom night guard or oral appliance if grinding or clenching is contributing to the problem
    • Addressing the underlying cause directly, whether that’s a TMJ disc issue, healing from a recent dental procedure, or an infection that needs treatment

    Most cases improve steadily over days to a couple of weeks with the right approach. It’s not something you have to simply push through on your own.

    If It Happened After a Dental Procedure

    If your jaw feels stiff or limited to open shortly after a dental appointment, particularly after a longer procedure or wisdom tooth removal, try not to panic. This is a recognized, temporary effect in some patients, caused by the muscles being held in one position for an extended period. Gentle movement, warm compresses, and time usually resolve it. If it isn’t easing up after a few days, or the discomfort feels like it’s getting worse rather than better, that’s worth a follow-up call to your dentist.

    Frequently Asked Questions

    Q: Can lockjaw go away on its own?

    A: Mild TMJ-related trismus sometimes eases with rest, gentle movement, and time. More persistent or painful cases benefit from a proper evaluation rather than waiting indefinitely, since addressing the underlying cause speeds up recovery considerably.

    Q: Is lockjaw the same as a locked jaw joint?

    A: They’re closely related but not identical. A “closed lock” specifically refers to a displaced TMJ disc physically blocking the joint, which is one particular cause of the broader symptom of trismus.

    Q: How common is tetanus today?

    A: It’s rare in places with routine vaccination access, but it hasn’t disappeared entirely, which is why deep wounds or punctures, especially if your tetanus booster isn’t current, are still worth taking seriously.

    Q: Should I see a dentist or a doctor for jaw locking?

    A: If the symptoms are confined to your jaw and face with no fever, spreading spasms, or recent wound involved, a dentist is the right first step. If there’s any sign it could be tetanus, emergency medical care comes first.

    Q: Can stress cause my jaw to lock?

    A: Yes, indirectly. Stress-related clenching and grinding put sustained strain on the jaw muscles and joint, which can contribute to episodes of trismus over time.

    TMJ and Jaw Care at C Dental Clinic

    Practitioner gently massaging a patient's jaw and face

    At C Dental Clinic in Al Nahda, Sharjah, jaw locking and TMJ-related discomfort are evaluated properly before any treatment is recommended, since the right approach depends entirely on what’s actually causing it. If your jaw has been feeling stuck, sore, or limited after a recent dental procedure or otherwise, it’s worth having it looked at rather than working around it.

    👉 Book a consultation at C Dental Clinic if your jaw pain or stiffness isn’t improving.

    References

    1. Cleveland Clinic — Trismus: Symptoms, Causes and Treatment
    2. National Institutes of Health — Trismus Overview
    3. Mayo Clinic — TMJ Disorders: Symptoms and Causes

  • Bleeding Gums When You Brush: Is It Gingivitis or Something Else?

    Bleeding Gums When You Brush: Is It Gingivitis or Something Else?

    Seeing a bit of pink in the sink after brushing is one of those moments people tend to explain away in half a second. Brushed too hard, probably. New toothbrush, maybe. It’s rarely the first thought that something might actually be wrong. But healthy gums, on their own, don’t bleed. If it’s happening regularly, even just now and then, it’s your mouth trying to tell you something, and it’s worth actually listening.

    The good news is that bleeding gums are usually caused by something very treatable. The less good news is that “usually” isn’t “always,” and telling the difference matters.

    The Most Common Cause: Gingivitis

    For the vast majority of people, bleeding gums point to gingivitis, the earliest and mildest stage of gum disease. It starts with plaque, a sticky film of bacteria that builds up along the gumline whenever brushing and flossing aren’t quite thorough enough. Left in place for even a few days, plaque begins to irritate the gum tissue, causing inflammation, redness, and the kind of bleeding that shows up when you brush or floss.

    Gingivitis symptoms tend to be fairly recognizable once you know what to look for:

    • Gums that bleed during brushing or flossing, even with gentle pressure
    • Redness or a deeper pink than the healthy pale pink of normal gum tissue
    • Mild swelling or puffiness along the gumline
    • Gums that feel tender to the touch
    • Breath that doesn’t fully freshen up even after brushing

    What makes gingivitis worth catching early is that, unlike more advanced gum disease, it’s fully reversible. The bone and tissue that anchor your teeth haven’t been damaged yet at this stage, so with better brushing habits, consistent flossing, and a professional cleaning or two, gingivitis genuinely goes away rather than just being managed.

    Why Gingivitis Often Gets Ignored

    Dentist examining a patient's teeth and gums during a dental checkup

    Part of the reason gingivitis is so widespread is that it typically doesn’t hurt. There’s no sharp pain pushing you toward the dentist, just a bit of bleeding that’s easy to dismiss as normal. That painless quality is exactly why it can quietly progress if nothing changes, not because the condition is dangerous on its own, but because plaque left untreated doesn’t stay in one place.

    When It’s More Than Gingivitis: Periodontitis

    If gingivitis goes unaddressed for long enough, the bacteria causing the inflammation can begin moving below the gumline, where it starts affecting the bone and connective tissue holding your teeth in place. At that point, it’s no longer gingivitis, it’s periodontitis, and the distinction matters because periodontitis causes damage that isn’t fully reversible the way early gingivitis is.

    Signs that bleeding might have progressed beyond gingivitis include:

    • Gums that appear to be pulling away or receding from the teeth
    • Teeth that feel slightly loose or shifted
    • Persistent bad breath that doesn’t improve with brushing
    • Pain when chewing, or a bite that suddenly feels different
    • Visible gaps forming between teeth that weren’t there before
    • Pus or discharge near the gumline

    Periodontitis is still treatable, usually through a deeper professional cleaning called scaling and root planing, sometimes alongside antibacterial treatment, but the goal shifts from reversing the condition to stopping it from progressing further and protecting what’s still healthy.

    Why Do Gums Bleed More When Flossing Specifically?

    Close-up of a person flossing between healthy teeth and along the gumline

    This comes up constantly, and it’s a fair question, especially for people who floss inconsistently. If your gums bleed noticeably more when flossing than brushing, it’s often simply because flossing reaches areas your toothbrush physically can’t, the tight spaces between teeth where plaque builds up fastest. Inflamed tissue in those spots bleeds more easily when finally disturbed.

    The common instinct is to stop flossing because it causes bleeding, but that tends to make things worse, not better. Skipping the area that’s already inflamed just gives plaque more time to build up further. In most cases, consistent daily flossing actually reduces the bleeding within one to two weeks, as the gum tissue heals and becomes less inflamed overall.

    When Bleeding Gums Aren’t About Gum Disease at All

    Gum disease explains most cases, but not all of them, and it’s worth knowing what else can be behind it, particularly if your oral hygiene is already solid and the bleeding still isn’t improving.

    Brushing technique. A toothbrush that’s too firm, or brushing with too much pressure, can irritate healthy gum tissue enough to cause occasional bleeding without any underlying disease at all.

    Hormonal changes. Shifts during puberty, pregnancy, or menopause can increase blood flow and sensitivity in gum tissue, making bleeding more likely even with an unchanged hygiene routine.

    Vitamin deficiencies. Low vitamin C or vitamin K can affect how well your gums heal and how easily they bleed, since both play a role in tissue health and normal clotting.

    Blood-related conditions. Less commonly, bleeding gums can be linked to conditions that affect blood clotting, or to certain blood-thinning medications, which make bleeding anywhere in the body, including the gums, more noticeable.

    Diabetes. Poorly managed blood sugar can make gum tissue more prone to inflammation and slower to heal, creating a cycle where gum disease and blood sugar control affect each other.

    Teeth grinding. In some cases, grinding or clenching puts enough pressure on gum tissue to contribute to irritation and bleeding around specific teeth.

    None of this means you should self-diagnose based on a list. It means that if bleeding continues despite genuinely good oral hygiene, it’s worth mentioning to a dentist rather than assuming it’s simply gum disease that hasn’t responded yet.

    What to Do If Your Gums Are Bleeding

    A few steps make a real difference for most people, particularly when caught at the gingivitis stage:

    1. Brush twice daily with a soft-bristled toothbrush, using gentle, circular motions rather than aggressive back-and-forth scrubbing
    2. Floss once a day, even if it causes some bleeding initially, since consistency is what actually resolves the inflammation
    3. Consider an antibacterial mouthwash if recommended by your dentist, which can help reduce the bacteria contributing to inflammation
    4. Book a professional cleaning, since plaque that’s hardened into tartar can’t be removed by brushing and flossing alone
    5. Track whether bleeding improves over one to two weeks of consistent care, which helps determine whether it’s simple gingivitis or something that needs a closer look

    Why Healthy Gums Matter Beyond Your Mouth

    Gum health isn’t purely a dental concern. Long-term gum inflammation has been studied in connection with several broader health areas, including how well diabetes is managed, cardiovascular health, and in some research, pregnancy outcomes. This doesn’t mean bleeding gums are automatically a sign of a serious systemic issue, but it’s part of why dentists take the symptom seriously rather than treating it as purely cosmetic.

    Frequently Asked Questions

    Q: Is it normal for gums to bleed a little every time I brush?

    A: No. Occasional light bleeding after a rougher brushing session can happen, but regular bleeding, even mild, usually points to gum inflammation that’s worth addressing rather than something to expect as normal.

    Q: How long does it take for gingivitis to heal?

    A: With consistent brushing and flossing, most people notice improvement within one to two weeks, though a professional cleaning speeds up recovery by removing plaque and tartar that home care can’t reach.

    Q: Should I stop flossing if it makes my gums bleed?

    A: No, that usually makes the underlying inflammation worse. Gentle, consistent flossing typically reduces bleeding within a couple of weeks as gum health improves.

    Q: Can stress cause bleeding gums?

    A: Indirectly, yes. Stress can weaken the immune response and, in some people, lead to teeth grinding, both of which can make gums more prone to irritation and bleeding.

    Q: When should I see a dentist about bleeding gums?

    A: If bleeding persists for more than two weeks despite good oral hygiene, or if you notice gum recession, loose teeth, or persistent bad breath alongside it, it’s time for a proper evaluation rather than waiting it out.

    Gum Health Care at C Dental Clinic

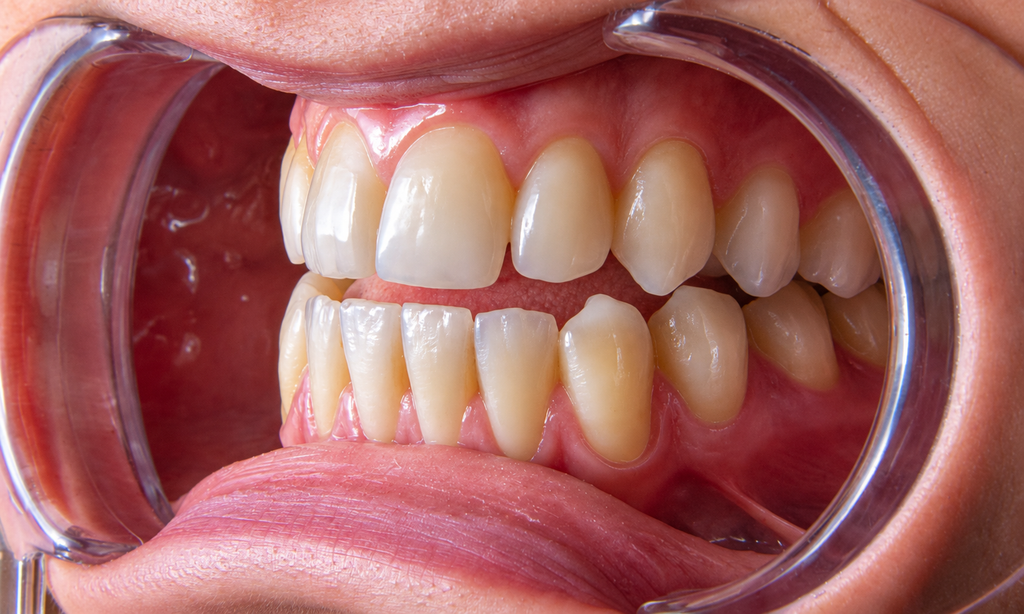
    Close-up view of teeth and gums using a dental cheek retractor

    At C Dental Clinic in Al Nahda, Sharjah, a gum evaluation looks at more than just whether bleeding is present, it considers your overall oral hygiene, any contributing habits, and whether what you’re experiencing points to early gingivitis or something that needs deeper treatment. Catching it early is really the whole game here, since gingivitis is fully reversible while periodontitis is not.

    👉 Book a consultation at C Dental Clinic if your gums have been bleeding regularly.

    References

    1. Cleveland Clinic — Bleeding Gums: Causes and Treatment
    2. Centers for Disease Control and Prevention — About Periodontal (Gum) Disease
    3. NCBI Bookshelf, InformedHealth.org — Overview: Gingivitis and Periodontitis

  • Night Guards for Teeth Grinding: Do You Really Need One?

    Night Guards for Teeth Grinding: Do You Really Need One?

    Waking up with a sore jaw or a dull headache you can’t quite explain is one of those things people tend to live with for months before mentioning it to anyone, let alone a dentist. It’s easy to blame a bad pillow, poor sleep, or just stress from the week. Sometimes that’s exactly what it is. Other times, the real cause is happening every night without you ever being awake for it.

    Teeth grinding, known clinically as bruxism, is far more common than most people realize, and a night guard is usually the first thing a dentist recommends once it’s identified. Whether you actually need one, though, depends on a few things worth understanding first.

    What Bruxism Actually Is

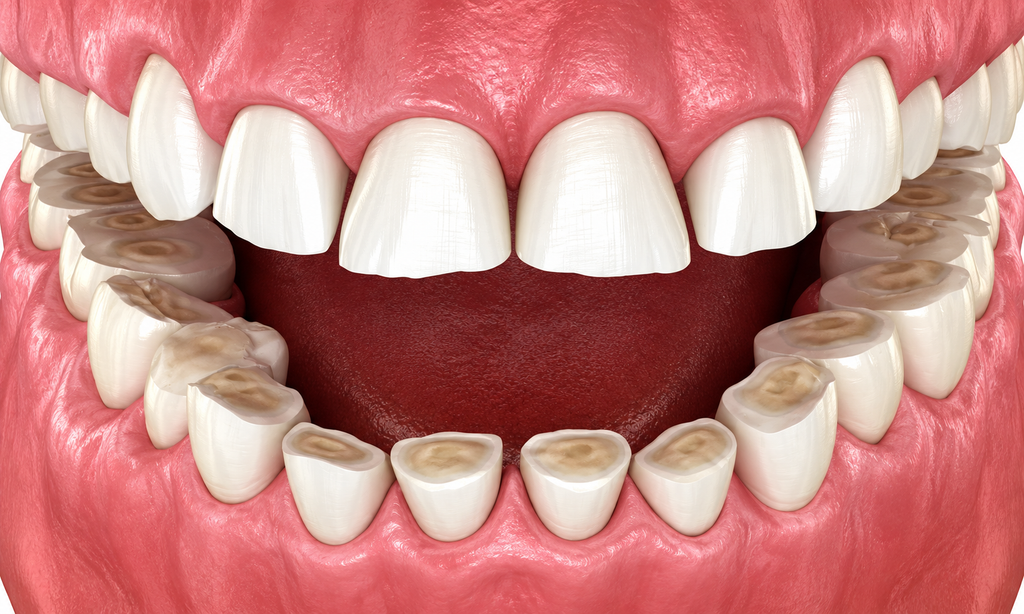
    Illustration of teeth showing enamel wear caused by bruxism

    Bruxism is the involuntary clenching, grinding, or gnashing of teeth, and it comes in two forms. Awake bruxism happens during the day, often tied to concentration, stress, or anxiety, and tends to show up as clenching rather than the back-and-forth grinding motion. Sleep bruxism happens at night, is classified as a sleep-related movement disorder, and is the type most people are completely unaware they’re doing until a partner mentions the sound, or a dentist spots the wear during a check-up.

    The exact cause isn’t fully understood, but a combination of factors tends to be involved: stress and anxiety, certain sleep disorders, misaligned teeth or an uneven bite, and in some cases, side effects from specific medications. There’s also a growing body of research linking sleep bruxism to obstructive sleep apnea, which is part of why persistent grinding sometimes warrants a broader look at sleep health, not just a dental one.

    Signs You Might Be Grinding Your Teeth

    Because sleep bruxism happens while you’re unconscious, most people find out indirectly, through symptoms rather than catching themselves in the act. Common signs include:

    • Waking up with a sore or tight jaw
    • Dull headaches, especially around the temples, first thing in the morning
    • Teeth that feel more sensitive than usual
    • Visible wear, flattening, or chipping on your teeth
    • A partner mentioning they’ve heard grinding sounds at night
    • Jaw clicking or discomfort that seems worse in the morning
    • Small indentations along the edges of your tongue
    • Occasional pain that feels like it’s coming from your ear, without any actual ear problem

    None of these symptoms alone confirms bruxism, since several overlap with other issues, but a pattern of two or three together is usually enough for a dentist to take a closer look during your next visit.

    Why It’s Worth Taking Seriously

    Occasional, mild grinding usually isn’t something to worry about, and plenty of people brux from time to time without it ever causing real damage. The concern is with frequent or intense grinding, which over months and years can lead to genuinely significant problems: worn-down enamel, cracked or chipped teeth, loosened teeth, and ongoing strain on the jaw joint that can contribute to temporomandibular joint issues.

    Left unaddressed long enough, the dental work needed to repair grinding-related damage tends to be far more involved, and more expensive, than the treatment that could have prevented it in the first place.

    How a Night Guard Actually Helps

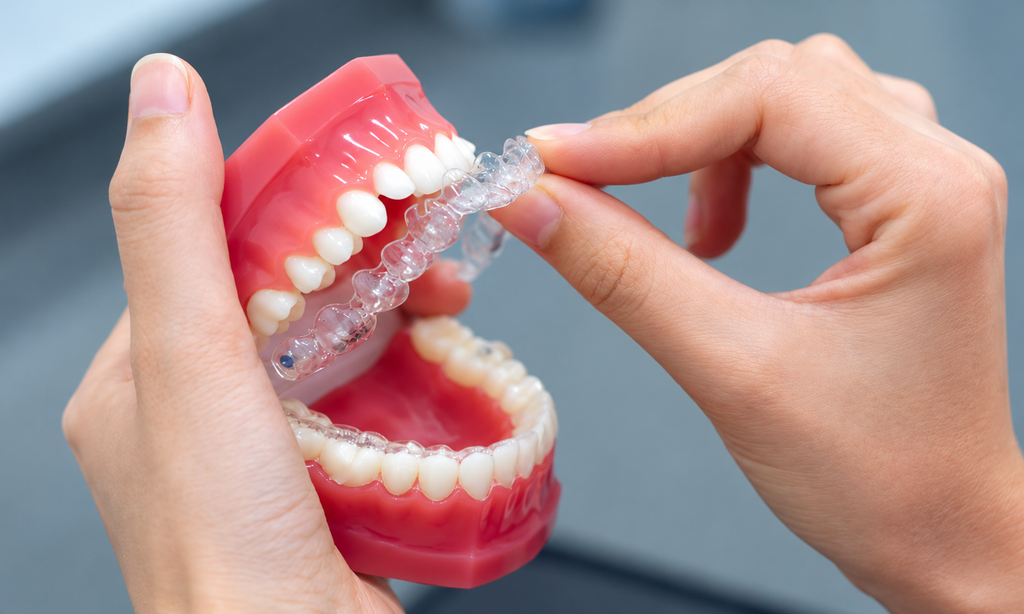
    Night guard being placed over a dental model showing upper and lower teeth

    A night guard, sometimes called a mouth guard or occlusal splint, is a device worn while sleeping that creates a physical barrier between your upper and lower teeth. It doesn’t stop the underlying urge to grind, but it absorbs and distributes the force so your teeth aren’t wearing directly against each other. Over time, this protects enamel from erosion, reduces the risk of chips and cracks, and for many patients, eases the muscle tension that leads to jaw soreness and morning headaches.

    Some night guards are also designed to slightly reposition the jaw into a more relaxed alignment, which can further reduce strain on the jaw joint and surrounding muscles, beyond just cushioning the teeth themselves.

    Custom Night Guards vs. Store-Bought Options

    This is a genuinely common question, since over-the-counter guards are cheap and easy to find at any pharmacy. They can offer some short-term relief, but they come with real trade-offs. Generic guards are bulkier, don’t fit the specific shape of your teeth or bite, and can actually be uncomfortable enough that people stop wearing them within weeks.

    A custom-fitted night guard, made from an impression of your own teeth, sits far more precisely, feels less intrusive, and lasts considerably longer with proper care. It’s also made with your specific bite and grinding pattern in mind, rather than a generic average. For anyone dealing with moderate to severe bruxism, or noticeable dental wear already, a custom guard is almost always the better long-term investment, both for comfort and for how well it actually protects your teeth.

    Do You Really Need One?

    Not everyone who occasionally clenches their jaw needs a night guard. If grinding is mild, infrequent, and not causing any symptoms or visible wear, your dentist may simply monitor it at future check-ups rather than recommend treatment right away.

    A night guard becomes genuinely worth it when:

    • You’re waking up with regular jaw pain or headaches
    • A dentist has noticed visible wear, flattening, or damage on your teeth
    • Your partner has mentioned hearing grinding at night
    • You already have cracked, chipped, or sensitive teeth that grinding could be making worse
    • Previous dental work, like crowns or fillings, is at risk of damage from ongoing grinding

    If any of that sounds familiar, it’s worth bringing up at your next appointment rather than waiting for damage to become obvious on its own.

    Beyond the Night Guard: Managing the Root Cause

    A night guard protects your teeth, but it doesn’t necessarily address why the grinding is happening in the first place, particularly when stress is a major factor. Alongside a night guard, a few things often help:

    • Stress management techniques, including relaxation exercises, better sleep habits, or even therapy for underlying anxiety
    • Cutting back on caffeine and alcohol, especially in the evening, since both are known to worsen grinding for some people
    • Addressing sleep quality generally, and getting evaluated for sleep apnea if grinding is paired with loud snoring or daytime fatigue
    • Correcting bite misalignment, if that’s identified as a contributing factor, through orthodontic or restorative treatment

    For most patients, the night guard and these broader lifestyle adjustments work together, rather than one replacing the other.

    Custom Mouth Guards in Sharjah at C Dental Clinic

    Close-up of a custom night guard being fitted over the teeth

    At C Dental Clinic in Al Nahda, Sharjah, a custom night guard starts with a proper evaluation, checking for the specific wear patterns, bite alignment, and jaw discomfort that point toward bruxism, rather than assuming every case looks the same. From there, an impression is taken and the guard is made to fit your teeth precisely, so it’s comfortable enough to actually wear every night, which is really where the protection comes from.

    Frequently Asked Questions

    Q: How long does it take to get used to wearing a night guard?

    A: Most people adjust within a week or two. It can feel unfamiliar at first, but a well-fitted custom guard is generally far more comfortable than people expect.

    Q: Will a night guard stop me from grinding my teeth entirely?

    A: Not necessarily. It protects your teeth from the damage grinding causes, but it doesn’t always eliminate the underlying habit, which is why addressing stress or other root causes alongside it matters.

    Q: How long does a custom night guard last?

    A: With proper care, a custom night guard typically lasts several years, though it should be checked periodically for wear, particularly if grinding is severe.

    Q: Can children need night guards too?

    A: Yes, teeth grinding is fairly common in children, though it often resolves on its own as adult teeth come in. A dentist can advise whether a guard is genuinely needed in a child’s case.

    Q: Is teeth grinding always caused by stress?

    A: Not always. While stress is a common trigger, sleep disorders, bite misalignment, and even certain medications can also play a role, which is part of why a proper evaluation matters rather than assuming stress is the only cause.

    When to Stop Ignoring It

    A sore jaw or a morning headache is easy to brush off as just another symptom of a busy week. But if it’s happening regularly, or your teeth are showing visible wear, it’s worth getting checked rather than waiting for the damage to become harder to reverse.

    👉 Book a consultation at C Dental Clinic to find out if a custom night guard is right for you.

    References

    1. Cleveland Clinic — Bruxism (Teeth Grinding): Symptoms, Causes and Treatment
    2. American Dental Association — Bruxism: Teeth Grinding
    3. Colgate Oral Care — Do I Need a Night Guard for Teeth Clenching?